Introduction
C-reactive protein (CRP) is an acute phase protein (APP), a term that describes proteins whose concentration changes in response to inflammation or immune system stimulation, regardless of the cause. CRP is generated quickly, with significant increases observed just a few hours after the inflammatory stimulus (e.g., 4 hours after a surgical intervention), and peak concentrations are reached at approximately 24 hours. This reaction is part of the innate immune response, which means that it is rapid and non-specific, and it can be triggered by any process that damages the animal [1]. After more than 20 years of using and providing external services for CRP measurement at our laboratory, we have found that practitioners who regularly use CRP consider it to be one of the most important biomarkers of inflammation. Included as a part of their routine analytical profiles, CRP assay is employed for periodic check-ups, diagnostics, treatment monitoring, and predicting the outcome of inflammatory disease. This review will provide updated information and practical examples on how CRP can be employed in clinical practice, and will follow the initial consensus based on a seven-point plan established some years ago about the use of CRP in companion animals [1].
Always use a validated assay
Any method used to assess CRP in practice must be validated to ensure the results can be trusted. Various manufacturers currently offer certified in-house (“benchtop”) canine-specific tests, and the larger clinical pathology laboratories also provide assays. Although certain human assays may not be suitable for dogs, others can be effective and provide a cost-efficient means of measuring CRP [2]. However, it is always to be recommended that standardization of the assay (using purified protein or pools of acute phase serum) and control samples should be of canine origin.
Serum, EDTA or heparinized plasma can be employed for CRP measurements, and because the protein is fairly stable, samples can be refrigerated for several days or frozen for long-term preservation. It is important to know the effect of hemolysis, lipemia and bilirubinemia on the CRP values obtained, as the effects can vary depending on the method used. In our laboratory, the reference range for CRP in healthy dogs is below 12 mg/L, and whilst this value can vary between laboratories, it is usually not higher than 20 mg/L. There are no evident changes in reference ranges due to age or gender, although in pregnant bitches CRP increases at 21 days after fertilization, coinciding with embryonic implantation.
Other APPs can be used alongside CRP
The possibility of using CRP along with other APPs will be considered later, but the different APPs will be described here. APPs that increase concentration after an inflammatory stimulus are known as POSITIVE APPs, while others that decrease after such a stimulus are called NEGATIVE APPs (Figure 1).
Positive APPs are further classified into two groups, namely major and moderate: Major APPs in dogs are CRP and serum amyloid A (SAA). While these proteins are present in low level in healthy animals, their concentration can increase by 10-100 times when stimulated. Moderate APPs are haptoglobin (Hp), ferritin and fibrinogen. Their concentrations increase 2-10-fold following stimulation. Major APPs exhibit a rapid increase in concentration followed by a steep decline, usually within hours, while moderate APPs take longer to both increase from and return to normal levels.
Albumin and paraoxonase-1 (PON-1) are examples of negative APPs. During inflammation, the albumin serum concentration decreases. This may be because albumin is the most abundant protein in serum, and its decrease can promote the synthesis of other proteins related to inflammation. PON-1 has an antioxidant function, and its decrease in inflammatory processes is possibly due to the associated oxidative stress that consumes this protein.

CRP for infection and inflammation
The main reason to use a CRP assay is to confirm or rule out an inflammatory or infectious process. Whilst the most widely used tool for detecting inflammation is the evaluation of white blood cells (WBCs), ideally CRP should be measured and interpreted at the same time. Moreover, CRP has several advantages over WBCs in detecting and evaluating the severity of inflammation, especially as it has better sensitivity. For example, higher sensitivity of CRP has been reported in cases of babesiosis (Figure 2) [3] or various surgical procedures [4], and this is particularly important where there is decreased bone marrow activity. In addition, CRP is highly stable, allowing for long-term storage of samples, which is not possible with WBCs.

Shutterstock
Whilst elevated CRP levels are very useful in detecting inflammation in the dog, it is important to note that a CRP within the reference range is also a significant clinical finding, as it suggests the absence of an acute inflammatory or infectious process. In addition to detect or rule out inflammation, CRP can also provide additional information for the clinician, as shown in Table 1.
Table 1. What information can CRP provide beyond detecting inflammation?
| Additional information | Examples |
| Evaluate the severity of the inflammation or inflammatory disease. This is because increases in CRP are usually related to the magnitude of the inflammation. |
|
| An increase in CRP in conditions where it is usually within the reference range may indicate the presence of complications or a severe form of the disease. |
|
José Cerón
CRP may aid identification of a possible etiology
Although CRP cannot identify the cause of inflammation, due to its non-specific nature, its magnitude of increase can help to narrow down the list of possible causes and guide the diagnostic process (Table 2; Figure 3). This can lead to various practical applications, as outlined in Table 3. In addition, it is important to note that there are situations where CRP may significantly aid in differentiating between the causes of a problem, such as:
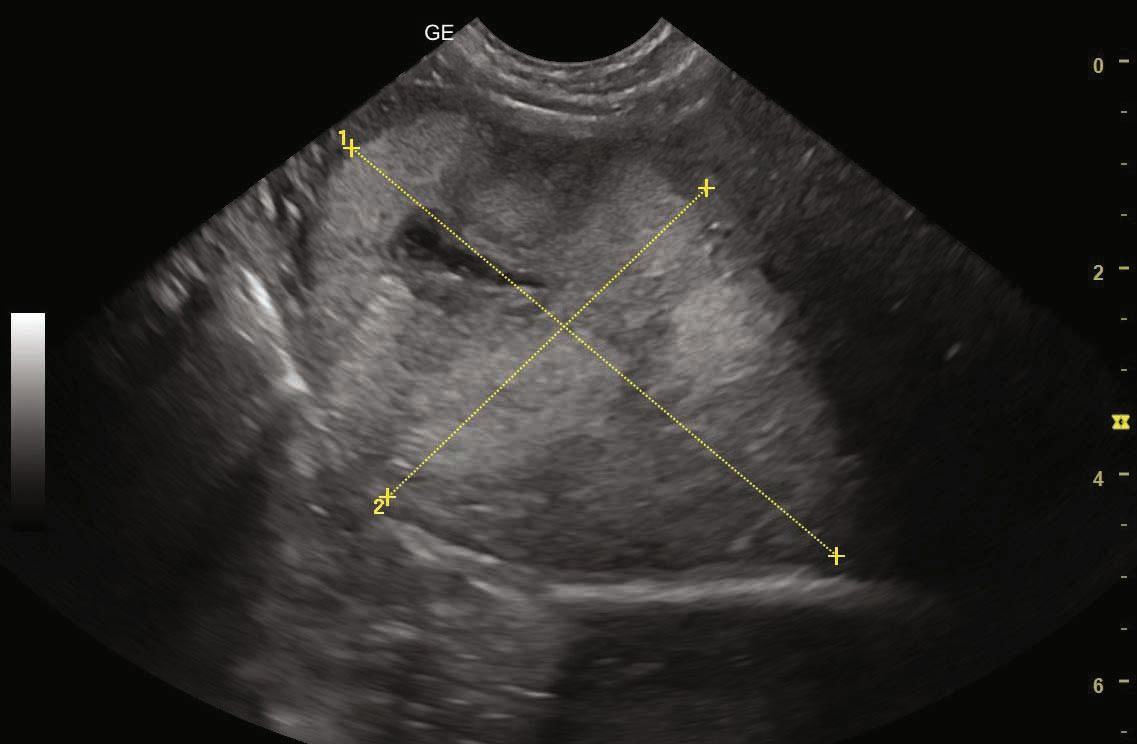
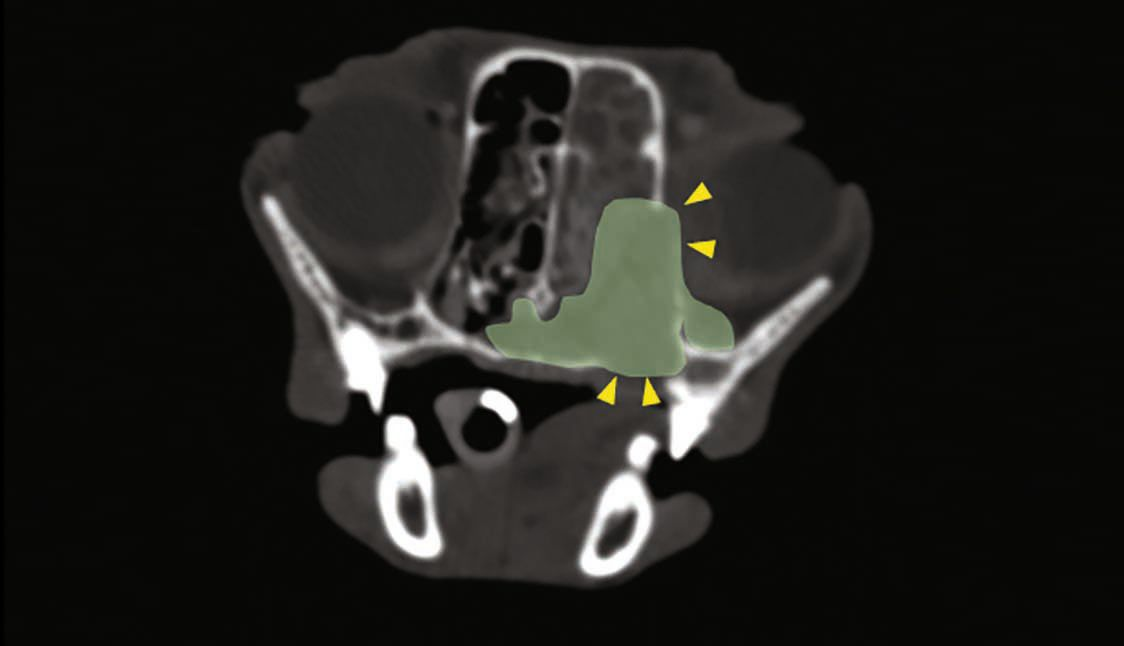
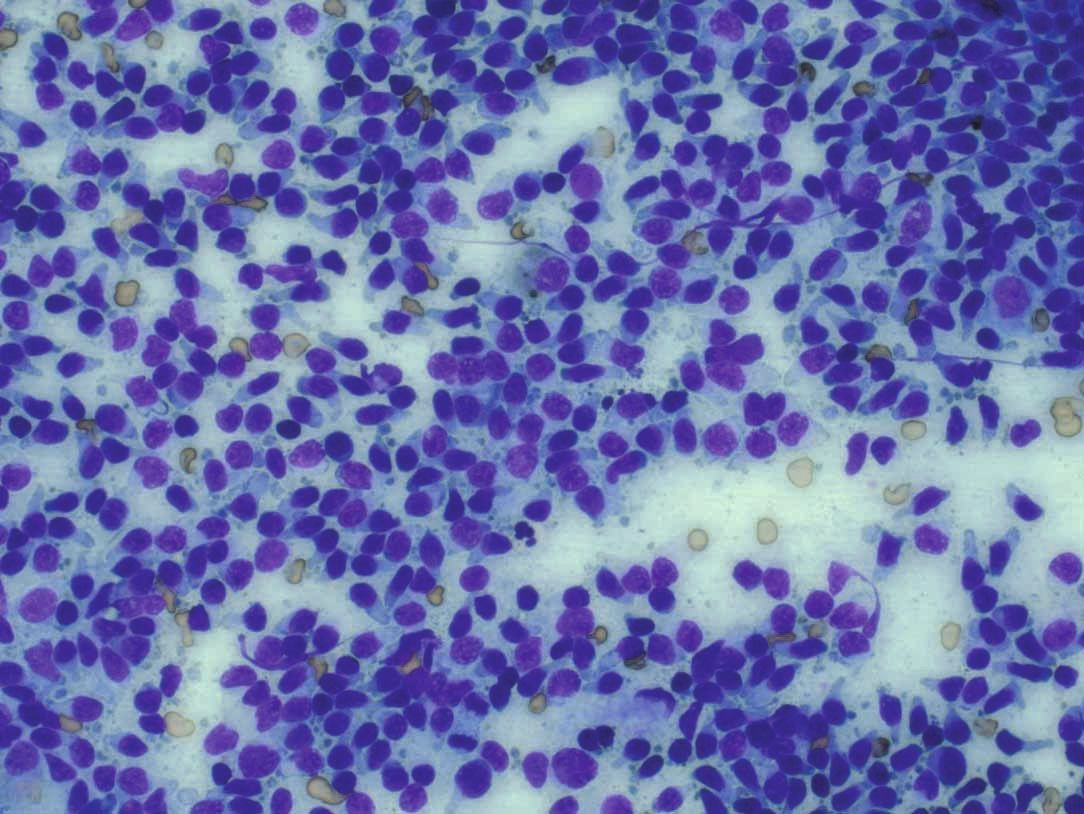
- Nasal disease: slight increases in CRP values have been observed in cases of aspergillosis, non-specific rhinitis, or neoplasia [17]. However, if there is a marked elevation in CRP levels in a dog with signs of nasal disease (Figure 4), it may indicate an underlying inflammatory problem that is of clinical significance.
- Gastrointestinal (GI) disease: some conditions that cause chronic GI signs in dogs, such as inflammatory bowel disease (IBD), parasitic infections, dietary and antibiotic responsive diarrhea, GI neoplasia or presumed motility disorders may not show marked increases in CRP [9]. Also, intestinal malabsorption caused by exocrine pancreatic insufficiency, wheat-sensitive enteropathy or anaerobic bacterial overgrowth has been reported not to produce increases in CRP in dogs [18]. Therefore, if there is a noticeable increase in CRP associated with any of these conditions, it can indicate the presence of a complicating systemic inflammatory condition.
Table 2. Clinical interpretation of the magnitude of serum CRP increase in dogs (from [11]).
| CRP (mg/L) | Comment |
| 0-12 | Normal (the reference range can vary depending on the laboratory) |
| 12-20 |
Slight increase of uncertain diagnostic value:
|
| 20-39 |
Increased levels:
|
| 40-100 |
Significantly increased levels:
|
| > 100 |
Severe inflammation:
|
Table 3. Potential usefulness of CRP in narrowing the list of causes and guiding diagnosis.
| Application and explanation | Examples |
| Suspicion of sepsis or immune-mediated disorder: Increases in CRP > 100 mg/L are usually associated with either SIRS, which in the case of a positive bacterial culture could indicate sepsis, or an immune-mediated disorder. |
|
| Suspicion of an infectious-inflammatory cause: Where clinical signs could be caused by either inflammatory or non-inflammatory factors... |
|
This point only refers to CRP measurement as a stand-alone test, but additional examples of how CRP can be used in combination with other APPs to identify the cause of certain conditions are discussed below.

Shutterstock
CRP helps monitor response to treatment
CRP values returning to normal levels in an infectious-inflammatory disease indicates that a dog is responding to treatment and implies a good prognosis. This has been demonstrated in numerous inflammatory diseases, such as acute pancreatitis, where CRP can be a useful tool for monitoring clinical progression and response to treatment [19]. CRP has been shown to better reflect the evolution of inflammation after treatment compared to WBCs in conditions such as immune-mediated polyarthritis, indicating periods of relapse and remission of the disease [20]. Examples of interpretation are:
- Positive response → decrease in CRP: If the dog’s initial CRP levels are high, a return to the reference range along with clinical improvement indicates that treatment can be stopped. In this way, antibiotic treatments can be greatly optimized. For instance, in a study involving dogs with bacterial pneumonia, the duration of antibiotic administration was significantly reduced when normalization of serum CRP was used to guide the treatment [21]. In this study, antibiotics were discontinued 5-7 days after serum CRP returned to normal, as opposed to the conventional approach of treating for 1-2 weeks beyond the resolution of alveolar density on thoracic radiographs. This reduction in treatment duration did not increase the number of relapses.
- Negative response → little or no decrease in CRP: The absence of a decrease in CRP after treatment would indicate that either the diagnosis or the treatment was inadequate, and should necessitate a thorough evaluation of the patient. This could be considered a “red-light” alert. For example, CRP levels after surgery are typically low by the time sutures are removed [4]. Therefore, an increase in CRP during the postoperative period may indicate the presence of complications, such as incision site infection that can appear after surgical treatment for pyometra.
CRP can predict the presence of an inflammatory-infectious disease
CRP’s high sensitivity and fast stimulation of response allow detection of subclinical inflammation, with changes in APPs occurring before clinical signs develop. Therefore, this protein is highly suitable for routine health checks, where an increase in APPs in an apparently healthy animal can indicate the presence of a subclinical disease or predict the development of active disease in the near future. For example, in a study on dogs infected with Babesia gibsoni, high concentrations of CRP were documented despite the absence of obvious clinical signs or parasitemia [22]. Similarly, high CRP values are reported in asymptomatic dogs infected with Leishmania infantum – and it can be assumed that these animals may develop clinical signs at a later stage [23].

Shutterstock
The future: APPs profiles
Divergences between major and moderate APPs can provide useful clinical information, so if possible, it is recommended to use a laboratory profile that includes at least one major and one moderate APP. The term “divergence” describes a situation where APPs of the two groups do not change as expected in the presence of an inflammatory stimulus. Some relevant examples are:
- ↑ Hp & ↔ CRP (increased Hp concentration with CRP values remaining in the reference range). Given that CRP usually shows a greater increase than Hp in an inflammatory situation, detecting this profile in a dog with no history of glucocorticoid treatment could indicate increased production of endogenous steroids. Glucocorticoids stimulate increases in haptoglobin and decreases in CRP [24], making this profile a potential indicator of canine hyperadrenocorticism. If a dog diagnosed with hyperadrenocorticism shows an increase in CRP, it indicates the presence of a severe inflammatory stimulus that can overcome the inhibitory effect of the endogenous corticosteroids. This may suggest the need to investigate potential inflammatory complications such as severe sepsis, urinary infection, deep pyoderma, severe mastitis or immune-mediated hemolytic anemia [24].
- ↔ Hp & ↑ CRP (steady or decreased levels of Hp accompanied by an increase in CRP levels). This profile may indicate hemolysis or internal hemorrhage leading to hemolysis. This is because Hp binds to hemoglobin released from damaged erythrocytes to facilitate its degradation and prevent the oxidative stress caused by hemoglobin; therefore, Hp can be consumed after hemolysis. As an example, in dogs naturally infected with B. canis, the concentration of CRP increased (mean value of 170 mg/L), while the concentration of Hp remained within the reference range (mean value of 2.7 g/L). The haptoglobin values could reflect the mixed effects of inflammation, which is associated with moderate increases, and hemolysis, which reduces the haptoglobin concentration [3].
- ↑ CRP & ↔ Ferritin (increased CRP and normal levels of ferritin). In canine pyometra there is a significant increase in serum CRP, indicating a severe inflammatory condition. However, serum ferritin, despite being a moderate positive APP, does not show a significant increase. This divergence in the dynamics of these APPs could be a useful tool for suspecting cases of this disease [25].
Asta Tvarijonaviciute
Conclusion
CRP is a valuable diagnostic tool in routine canine practice and is an excellent assay to incorporate when testing both in disease situations and in routine health screens. It is expected that the information present in this paper will assist practitioners already using CRP to maximize its benefits, and encourage those unfamiliar with CRP to consider its applications [1].
| Conflict of interest statement; Neither author has a financial or personal relationship with other people or organizations that could inappropriately influence or bias the content of the paper. |
AcknowledgementThe authors would like to dedicate this work to Dr. Marco Caldin, one of the pioneers and main contributors to the application of CRP in canine practice; his vision, knowledge and legacy is a continuous source of inspiration to us and other many researchers in this field. The authors would also like to thank Silvia Martinez-Subiela for her advice and help in the preparation of this manuscript. |

José Cerón
DVM, PhD, Dip. ECVCP, Interdisciplinary Laboratory of Clinical Analysis (Interlab-UMU), Campus Mare-Nostrum, University of Murcia, Spain
Spain
Dr. Cerón is a full professor at Murcia University Veterinary School and Diplomate of the European College of Veterinary Clinical Pathology. He serves as Head of the Veterinary Diagnostic Laboratory of Murcia University (INTERLAB-UMU), providing routine services to the teaching hospital, external practitioners and private companies. He is a past president of the European Society of Veterinary Clinical Pathology and has published more than 400 papers related to laboratory analysis in international journals.

Asta Tvarijonaviciute
DVM, PhD, Interdisciplinary Laboratory of Clinical Analysis (Interlab-UMU), Campus Mare-Nostrum, University of Murcia, Spain
Spain
Dr. Tvarijonaviciute is currently a lecturer in the Small Animal Internal Medicine Service at Murcia University Veterinary Teaching Hospital. She is accredited in internal medicine by the Spanish Association of Veterinarians Specialists in Small Animals, and has research interests centered around the practical application of biomarkers for health assessment in clinical settings.
References
- Cern JJ. Acute phase proteins, saliva and education in laboratory science: an update and some reflections. BMC Vet. Res. [Internet]. 2019;15(1):197. Available from: https://pubmed.ncbi.nlm.nih.gov/31189466/
- Muoz Prieto A, Tvarijonaviciute A, Escribano D, et al. Use of heterologous immunoassays for quantification of serum proteins: The case of canine C-reactive protein. PLoS One 2017;12(2);e0172188. Available from: https://pubmed.ncbi.nlm.nih.gov/28222144
- Matijatko V, Mrljak V, Ki I, et al. Evidence of an acute phase response in dogs naturally infected with Babesia canis. Vet. Parasitol. 2007;144(3-4):242-250. Available from: https://pubmed.ncbi.nlm.nih.gov/17116368/
- Yamamoto S, Shida T, Miyaji S, et al. Changes in serum C-reactive protein levels in dogs with various disorders and surgical traumas. Vet. Res. Commun. 1993;17(2):85-93. Available from: https://pubmed.ncbi.nlm.nih.gov/8212527/
- Mylonakis ME, Cern JJ, Leontides L, et al. Serum acute phase proteins as clinical phase indicators and outcome predictors in naturally occurring canine monocytic ehrlichiosis. J. Vet. Intern. Med. 2011;25(4):811-817. Available from: https://pubmed.ncbi.nlm.nih.gov/21564293/
- Tecles F, Caldn M, Zanella A, et al. Serum acute phase protein concentrations in female dogs with mammary tumors. J. Vet. Diagn. Invest. 2009;21(2):214-219. Available from: https://pubmed.ncbi.nlm.nih.gov/19286500/
- Manachai N, Umnuayyonvaree D, Punyathi P, et al. Impact of serum C-reactive protein level as a biomarker of cancer dissemination in canine lymphoid neoplasia. Vet. World 2022;15(12):2810-2815. Available from: http://www.ncbi.nlm.nih.gov/pubmed/36718344
- Martnez-Subiela S, Bernal LJ, Tvarijonaviciute A, et al. Canine demodicosis: the relationship between response to treatment of generalized disease and markers for inflammation and oxidative status. Vet. Dermatol. 2014;25(2):72-76, e23-4. Available from: https://pubmed.ncbi.nlm.nih.gov/24800264/
- McCann TM, Ridyard AE, Else RW, et al. Evaluation of disease activity markers in dogs with idiopathic inflammatory bowel disease. J. Small Anim. Pract. 2007;48(11):620-625.
- Segarra S, Martnez-Subiela S, Cerd-Cullar M, et al. Oral chondroitin sulfate and prebiotics for the treatment of canine inflammatory bowel disease: A randomized, controlled clinical trial. BMC Vet. Res. 2016;10:12(1);49.
- Cern JJ, Martinez-Subiela S, Tecles F, et al. Acute phase proteins in diagnostics: more than expected. J. Hellenic Vet. Med. Soc. 2017;65(3):197-204. Available from: https://ejournals.epublishing.ekt.gr/index.php/jhvms/article/view/15535
- Viitanen SJ, Laurila HP, Lilja-Maula LI, et al. Serum C-reactive protein as a diagnostic biomarker in dogs with bacterial respiratory diseases. J. Vet. Intern. Med. 2014;28(1):84-91. Available from: https://pubmed.ncbi.nlm.nih.gov/24351049/
- Kocaturk M, Martinez S, Eralp O, et al. Prognostic value of serum acute-phase proteins in dogs with parvoviral enteritis. J. Small Anim. Pract. 2010;51(9):478-483. Available from: https://pubmed.ncbi.nlm.nih.gov/20630018/
- Ohno K, Yokoyama Y, Nakashima K, . C-reactive protein concentration in canine idiopathic polyarthritis. J. Vet. Med. Sci. 2006;68(12):1275-1279. Available from: https://pubmed.ncbi.nlm.nih.gov/17213695/
- Bathen-Noethen A, Carlson R, Menzel D, et al. Concentrations of acute-phase proteins in dogs with steroid responsive meningitis-arteritis. J. Vet. Intern. Med. 2008;22(5):1149-1156. Available from: https://pubmed.ncbi.nlm.nih.gov/18691368/
- Fransson BA, Karlstam E, Bergstrom A, et al. C-reactive protein in the differentiation of pyometra from cystic endometrial hyperplasia/mucometra in dogs. J. Am. Anim. Hosp. Assoc. 2004;40(5):391-399. Available from: https://pubmed.ncbi.nlm.nih.gov/15347619/
- Sheahan D, Bell R, Mellanby RJ, et al. Acute phase protein concentrations in dogs with nasal disease. Vet. Rec. 2010;167(23):895-899. Available from: https://pubmed.ncbi.nlm.nih.gov/21262672/
- Caspi D, Snel FW, Batt RM, et al. C-reactive protein in dogs. Am. J. Vet. Res. 1987;48(6):919-921.
- Holm JL, Rozanski EA, Freeman LM, et al. C-reactive protein concentrations in canine acute pancreatitis. J. Vet. Emerg. Crit. Care. 2004;14(3):183-186. Available from: https://onlinelibrary.wiley.com/doi/full/10.1111/j.1534-6935.2004.04010.x
- Kjelgaard-Hansen M, Jensen A, Houser GA, et al. Use of serum C-reactive protein as an early marker of inflammatory activity in canine type II immune-mediated polyarthritis: case report. Acta Vet. Scand. 2006;48(1);9. Available from: https://pubmed.ncbi.nlm.nih.gov/16987405/
- Viitanen SJ, Lappalainen AK, Christensen MB, et al. The utility of acute-phase proteins in the assessment of treatment response in dogs with bacterial pneumonia. J. Vet. Intern. Med. 2017;31(1):124-133. Available from: https://pubmed.ncbi.nlm.nih.gov/28032360/
- Suzuki K, Wakabayashi H, Takahashi M, et al. A possible treatment strategy and clinical factors to estimate the treatment response in Babesia gibsoni infection. J. Vet. Med. Sci. 2007;69(5):563-568. Available from: https://pubmed.ncbi.nlm.nih.gov/17551236/
- Cern JJ, Pardo-Marin L, Caldin M, et al. Use of acute phase proteins for the clinical assessment and management of canine leishmaniosis: general recommendations. BMC Vet. Res. 2018;14(1):196. Available from: https://pubmed.ncbi.nlm.nih.gov/29925385/
- Caldin M, Tasca S, Carli E, et al. Serum acute phase protein concentrations in dogs with hyperadrenocorticism with and without concurrent inflammatory conditions. Vet. Clin. Pathol. 2009;38(1):63-68. Available from: https://pubmed.ncbi.nlm.nih.gov/19228354/
- Cern JJ, Pardo-Marin L, Wdowiak A, et al. Divergences between serum C-reactive protein and ferritin concentrations in canine pyometra. BMC Vet. Res. 2023;19(1):1-6. Available from: https://bmcvetres.biomedcentral.com/articles/10.1186/s12917-023-03630-3